
Rotator cuff injury
Get your shoulder lifting, reaching and sleeping properly again
Reaching for a seatbelt, hanging out washing or rolling onto that shoulder at night sends a sharp catch of pain through it. Most rotator cuff injuries respond well to a structured physiotherapy program without surgery.
Medicare, NDIS, DVA and private health funds accepted.
Understanding Rotator cuff injury
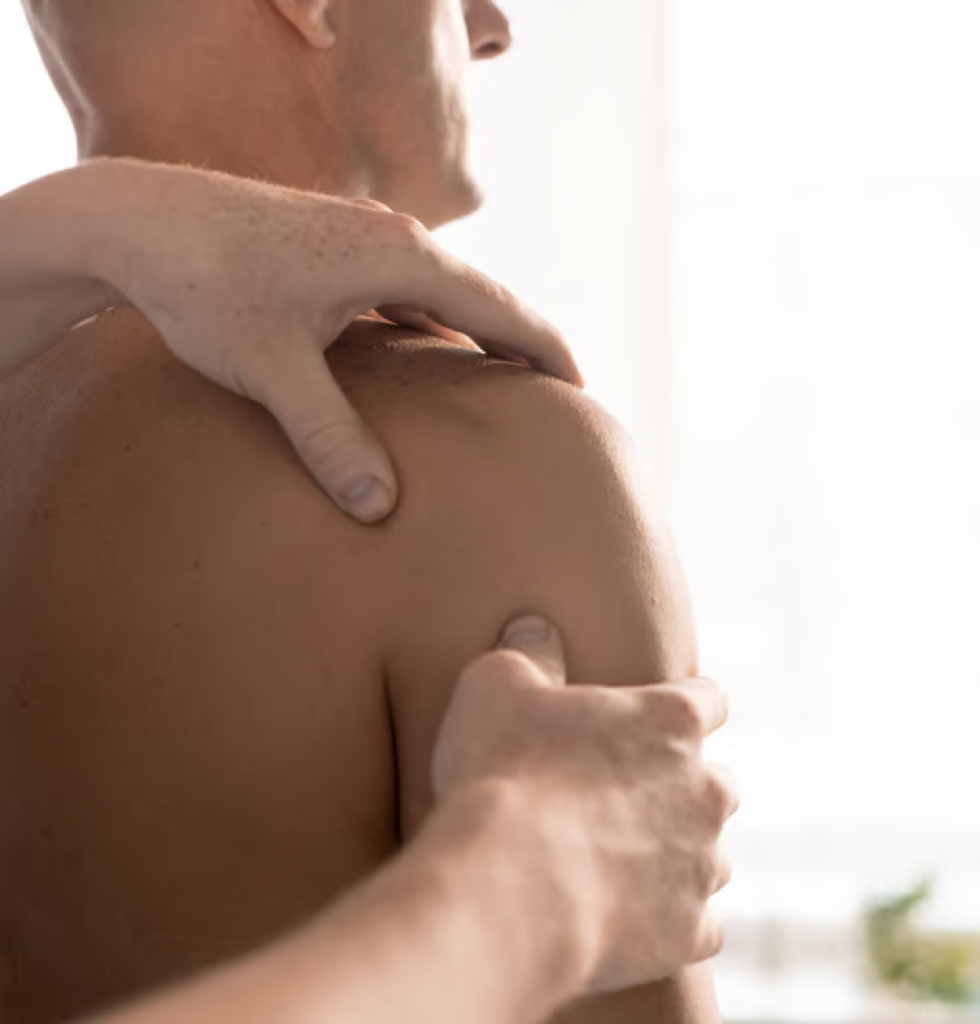
A rotator cuff injury is damage to the group of four muscles and tendons that hold your shoulder joint in place and control how your arm moves. It ranges from tendon overload and inflammation through to partial and full-thickness tears.
Your physiotherapist assesses which part of the cuff is involved and how much strength you have lost, then builds a loading program that rebuilds the tendon’s capacity. Most people improve without surgery.
Who does it affect?
overhead workers, throwing and swimming athletes, gym-goers, and anyone over 40, with risk rising each decade
How common is it?
rotator cuff–related shoulder pain is the most common type of shoulder pain, accounting for a large proportion of shoulder presentations.
What is the recovery like?
varies with the type and size of the injury, from several weeks for tendon overload to several months after a significant tear
Who should I see for treatment?
your physiotherapist, with referral to a GP or shoulder specialist when imaging or a surgical opinion is needed
What funding options are available?
Medicare, NDIS, DVA and private health funds accepted
What is a rotator cuff injury?
Your rotator cuff is a set of four muscles that wrap around the top of your arm bone and hold it centred in the shoulder socket. Their tendons let you lift, rotate and steady your arm.
Injuries can happen in many ways. A sudden load, such as a fall onto an outstretched hand or catching a heavy object, can tear a tendon outright. More often the tendon is loaded faster than it can adapt over weeks or months, becomes painful and weak, and can eventually fray..
Common contributing factors include:
A rapid jump in overhead work, throwing, swimming or pressing in the gym
Age-related change in the tendon, which reduces its tolerance to load
Weakness or poor control through the shoulder blade and upper back
A previous shoulder injury, dislocation or long period of immobility
Symptoms of Rotator cuff injury
Pain on the outside or front of the shoulder, sometimes spreading to the upper arm
A sharp catch when you lift your arm out to the side or reach behind you
Weakness when lifting, carrying, reaching overhead or doing up a bra strap
Pain lying on that side, which wakes you or stops you settling
Clicking, grinding or a feeling that the shoulder is not tracking properly
An arm that feels heavy or unreliable after a fall or a sudden pull
Your treatment plan follows your assessment, because a tendon under too much load and a torn tendon need different approaches.
What to expect at your first appointment
Tell us what is going on
How the pain started, what you cannot do, how you sleep, and what your work and sport demand of the shoulder.
A full assessment
Your physiotherapist tests your range, strength and specific cuff tendons, and checks your neck and shoulder blade control.
A clear plan
You get an explanation of which structure is involved, your first exercises, and what to change in the short term.
Review and adjust
Progress is measured by strength and function, and your program is loaded up as the shoulder responds.

When to book an appointment
Shoulder pain is limiting your movement, strength or everyday activities, or keeps returning when you increase activity
You cannot sleep on that side, reach overhead or lift at work
Rest, ice and anti-inflammatories have not changed anything
You are not sure whether it is the rotator cuff, your neck or the joint
Book an assessment if:
Looking after yourself at home
These steps support your program between appointments.
A rapid jump in overhead work, throwing, swimming or pressing in the gym
Age-related change in the tendon, which reduces its tolerance to load
Weakness or poor control through the shoulder blade and upper back
A previous shoulder injury, dislocation or long period of immobility

Meet the team who treat this
Behind every appointment is a team of practitioners who know each other, trust each other and work together for you. Across seven clinics and nine disciplines, our team shares expertise, coordinates treatment plans and celebrates your progress together.

Aimee Fuller
Healthcare Support Officer
Available at Blaxland

Alicia Whiticker
Healthcare Support Officer
Available at Blaxland

Amanda Banks
Healthcare Support Officer
Available at Blaxland

Amanda Duggan
Healthcare Support Officer
Available at Blaxland

Amy Meekings
Healthcare Support Officer
Available at Blaxland

Anita Beerapu
Healthcare Support Officer
Available at Blaxland

Benjamin Tucker
Healthcare Support Officer
Available at Blaxland

Blake Cossar
Healthcare Support Officer
Available at Blaxland

Bronte Tupper
Healthcare Support Officer
Available at Blaxland

Chris Farrugia
Healthcare Support Officer
Available at Blaxland

Corrina Aitken
Healthcare Support Officer
Available at Blaxland

David Logue
Healthcare Support Officer
Available at Blaxland

Dean Gresser
Healthcare Support Officer
Available at Blaxland

Emma Nassif
Healthcare Support Officer
Available at Blaxland

Esha Sharma
Healthcare Support Officer
Available at Blaxland

Fatima Hussaini
Healthcare Support Officer
Available at Blaxland

Felicity Spencer-Davey
Healthcare Support Officer
Available at Blaxland

Frankie Raikadroka
Healthcare Support Officer
Available at Blaxland

Hannah Norrie
Healthcare Support Officer
Available at Blaxland

Heather Edwards
Healthcare Support Officer
Available at Blaxland

Isaac Vella
Healthcare Support Officer
Available at Blaxland

Jarrah Nesbitt
Healthcare Support Officer
Available at Blaxland

Jonathan Lopez
Healthcare Support Officer
Available at Blaxland

Justin Hanna
Healthcare Support Officer
Available at Blaxland

Kasey Collins
Healthcare Support Officer
Available at Blaxland

Katrina Gauci
Healthcare Support Officer
Available at Blaxland

Kennedy Touet
Healthcare Support Officer
Available at Blaxland

Kristy Edwards
Healthcare Support Officer
Available at Blaxland

Kyle Perry
Healthcare Support Officer
Available at Blaxland

Lorna Nicastri
Healthcare Support Officer
Available at Blaxland

Maja Bosic
Healthcare Support Officer
Available at Blaxland

Marxy Koronel
Healthcare Support Officer
Available at Blaxland

Matt Barton
Healthcare Support Officer
Available at Blaxland

Michael Todd
Healthcare Support Officer
Available at Blaxland

Mr Jeffery Jenkins FACPS
Healthcare Support Officer
Available at Blaxland

Nathan Cavanagh
Healthcare Support Officer
Available at Blaxland

Patrick Celeban
Healthcare Support Officer
Available at Blaxland

Praise Khin
Healthcare Support Officer
Available at Blaxland

Sarah Bonnici
Healthcare Support Officer
Available at Blaxland

Shannon Smith
Healthcare Support Officer
Available at Blaxland

Siobhan Kelly
Healthcare Support Officer
Available at Blaxland

Taleisha Bozzi
Healthcare Support Officer
Available at Blaxland

Trystan Singh
Healthcare Support Officer
Available at Blaxland

Uty Kotwal
Healthcare Support Officer
Available at Blaxland

Yoni Hochberg
Healthcare Support Officer
Available at Blaxland

Zak Lloyd
Healthcare Support Officer
Available at Blaxland
EPC, DVA, NDIS and WorkCover welcome
Nearly half of our appointments are funded through Medicare, DVA, NDIS or WorkCover. We manage the paperwork so you can focus on your health.


NDIS
We support eligible NDIS participants across podiatry, physiotherapy, exercise physiology, dietetics and psychology, depending on your plan and goals. Eligibility and funding are set by your plan.

Medicare
Medicare may rebate podiatry, physiotherapy, exercise physiology and dietetics sessions when your GP refers you under an Enhanced Primary Care (EPC) or Chronic Disease Management (CDM) plan, and psychology sessions under a Mental Health Care Plan. The number of sessions is set by your plan.

DVA
Gold and White card holders can access DVA-funded care across our services with a valid referral.

WorkCover
If you have been injured at work, we accept WorkCover referrals for physiotherapy, exercise physiology and psychology, and manage the paperwork with your insurer, with a clear return-to-work plan.
Seven clinics across three regions
Find a clinic near you. Each location is staffed by local practitioners who know your community.
Penrith
Western SydneyOur largest centre, with our full range of services under one roof.
Ropes Crossing
Western SydneyPodiatry, at Ropes Crossing Village.
Blaxland
Blue MountainsPodiatry, physiotherapy, exercise physiology and group classes.
Springwood
Blue MountainsPodiatry, dietetics and a boutique footwear store.
Katoomba
Blue MountainsPodiatry, physiotherapy and dietetics, in a restored 1914 cottage.
Ryde
North ShorePodiatry, physiotherapy, dietetics and exercise physiology, with a footwear store and gait analysis.
Lindfield
North ShorePodiatry, with mobile podiatry across the North Shore and Northern Beaches.
Ready to get your shoulder working again?
Book a physiotherapy assessment and find out what your rotator cuff needs.
















Frequently asked questions
Which muscles make up the rotator cuff?
Four muscles form the rotator cuff: supraspinatus, infraspinatus, teres minor and subscapularis. They run from your shoulder blade to the top of your arm bone. Supraspinatus lifts the arm out to the side and is the most commonly injured. Infraspinatus and teres minor rotate the arm outwards, and subscapularis rotates it inwards. Your physiotherapist tests each one separately.
Can a rotator cuff tear heal without surgery?
A torn tendon does not usually knit back together on its own, but many people regain full function without surgery. The surrounding cuff muscles and shoulder blade muscles can be trained to take over the work, which reduces pain and restores strength. Surgery is more often considered for younger people with a traumatic tear, or when a well-run rehabilitation program has not restored the function you need.
What is the difference between a partial and a full-thickness tear?
A partial tear involves some fibres of the tendon while the rest remain attached. A full-thickness tear goes all the way through, so the tendon no longer pulls on the bone at that point. Full-thickness tears are more likely to cause obvious weakness. Both types can be painful, and pain level is a poor guide to tear size.
Can a rotator cuff injury cause pain down my arm?
Yes. Rotator cuff pain is commonly felt over the outside of the upper arm, roughly where a shirt sleeve ends, rather than in the joint itself. It rarely travels past the elbow. Pain that runs into the forearm and hand, or comes with pins and needles and numbness, more often points to the neck, and your physiotherapist will screen for this.
Should I wear a sling?
Not usually. Prolonged sling use lets the shoulder stiffen and the cuff muscles waste, which makes rehabilitation harder. A sling is sometimes used briefly after a traumatic injury or surgery, on specific advice. For most rotator cuff injuries you are better off using the arm within a comfortable range and avoid the positions that provoke sharp pain.
Are rotator cuff injuries more common as you get older?
Yes. Tendon tissue becomes less elastic and slower to repair with age, so cuff tears become more common from your forties onwards. Many older adults have tendon changes on imaging with no pain at all. That is why treatment focuses on your strength, movement and symptoms rather than on scan findings alone.